Monday, March 1, 2010

Renal Calculi/Kidney stone
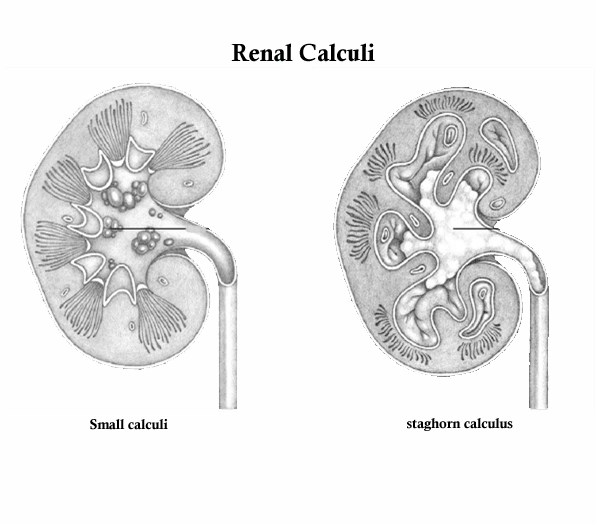
Renal Calculi/Kidney stones. Renal calculi, or nephrolithiasis, Kidney stones, are stones that form in the kidneys from the crystallization of minerals and other substances that normally dissolve in the urine. Renal calculi vary in size, with 90% less than 5 mm in diameter; some, however, grow large enough to prevent the natural passage of urine through the ureter. Renal calculi can form anywhere in the urinary tract, but they most commonly develop in the renal pelvis or calyces. Calculi may be solitary or multiple. Usualy these stones are composed of calcium salts. Other types are the struvite stones (which contain magnesium, ammonium, and phosphate), uric acid stones, and cystine stones. If the calculi remain in the renal pelvis or enter the ureter, they can damage renal parenchyma (functional tissue). Larger calculi can cause pressure necrosis. In certain locations, calculi cause obstruction, lead to hydronephrosis, and tend to recur. Renal calculi more common in males than females and are rare in blacks and children 

Causes for Renal Calculi/Kidney Stones
The precise cause of renal calculi is unknown, although Renal Calculi/Kidney stones are associated with dehydration, urinary obstruction, calcium levels, and other factors. 

  • Metabolic conditions such as renal tubular acidosis, elevated serum uric acid levels Hyperparathyroidism, renal tubular acidosis, elevated uric acid, defective metabolism of oxalate, a genetically caused defect in metabolism of cystine, and excessive intake of vitamin D or dietary calcium may predispose a person to renal calculi. 
  • Urinary tract infections associated with alkaline urine have been linked with calculus formation. Cystine stones are associated with hereditary renal disease 
  • Dehydration. Decreased water excretion concentrates calculus-forming substances. Patients who are dehydrated have decreased urine, with heavy concentrations of calculus-forming substances. Urinary obstruction leads to urinary stasis, a condition that contributes to calculus formation. 
  • Infection. Infected, scarred tissue may be a site for calculus development. In addition, infected calculi (usually magnesium ammonium phosphate or staghorn calculi) may develop if bacteria serve as the nucleus in calculus formation. Struvite calculus formation commonly results from Proteus infections, which may lead to destruction of renal parenchyma. 
  • Changes in urine pH. Consistently acidic or alkaline urine may provide a favorable medium for calculus formation, especially for magnesium ammonium phosphate or calcium phosphate calculi. 
  • Obstruction. Urinary stasis allows calculus constituents to collect and adhere, forming calculi. Obstruction also encourages infection, which compounds the obstruction. 
  • Immobilization. Immobility from spinal cord injury or other disorders allows calcium to be released into the circulation and, eventually, to be filtered by the kidneys. 
  • Renal Calculi/Kidney stones occur more often in men than in women 


Complications for Renal Calculi/Kidney stones
Calculi either remain in the renal pelvis and damage or destroy renal parenchyma, or they enter the ureter; large calculi in the kidneys cause pressure necrosis. Calculi in some sites cause obstruction, with resultant hydronephrosis, and tend to recur. Intractable pain and serious bleeding also can result from calculi and the damage they cause. 
Possible Complications for Renal Calculi/Kidney stones: 

  • Decrease or loss of kidney function 
  • Scarring, Kidney damage, 
  • Obstruction of the ureter (acute unilateral obstructive uropathy) 
  • stones Recurrence 
  • Urinary tract infection (UTI) 
  • renal colic 


Nursing Diagnosis for Renal Calculi/Kidney stones 
Nursing Diagnosis nursing care plans for Renal Calculi/Kidney stones determine by what we found in nursing assessment. Nursing Assessment nursing care plans for Renal Calculi/Kidney stones Typically, assessment findings vary depends with the size, location, and cause of the calculi: 
Patient history reveals a history of pain, and determine the intensity, duration, and location of the pain. The location of the pain varies according to the placement of the stone. The pain usually begins in the flank area but later may radiate into the lower abdomen and the groin. Ask if the pain had a sudden onset. Patients may relate a recent history of hematuria, nausea, vomiting, and anorexia. In cases in which a urinary tract infection is also present, the patient may report chills and fever. Determine the patient’s history to identify risk factors 
Physical Examination. Common symptom of renal calculi is severe pain, also referred as renal colic, which usually results from obstruction of large, rough calculi occlude the opening to the ureteropelvic junction and increase the frequency and force of peristaltic contractions. Pain intensity fluctuates and may be excruciating at its peak. 
Patient with calculi in the renal pelvis and calyces may complain of more constant, dull pain. He may also report pain and severe abdominal pain. The patient with severe pain also typically complains of nausea, vomiting and, possibly, fever and chills. Hematuria occur when calculi abrade a ureter, abdominal distention and, rarely, anuria 
Inspection reveals a patient in intense pain who is unable to maintain a comfortable position. Assess the patient for bladder distension. Monitor the patient for signs of an infection such as fever, chills, and increased white blood cell counts. Assess the urine for hematuria. Auscultate the patient’s abdomen for normal bowel sounds. Palpate the patient’s flank area for tenderness. Percussion of the abdominal area is normal, but percussion of the costovertebral angle elicits severe pain. 
Psychosocial Assessment: Patients with renal calculi may be extremely anxious because of the sudden onset of severe pain of unknown origin. Assess the patient’s ability to cope. Since diet and lifestyle may contribute to the formation of calculi, the patient may face lifestyle changes. Assess the patient’s ability to handle such changes. 

Diagnostic tests
Kidney-ureter-bladder (KUB) radiography, and Excretory urography, retrograde pyelography, Abdominal computed tomography scan, or Abdominal or kidney magnetic resonance imaging Kidney ultrasonography. Urine culture of a midstream Evaluated A 24-hour urine 
Other diagnostic test: Serial blood calcium and phosphorus levels indicate hyperparathyroidism and show an increased calcium level in proportion to normal serum protein levels. Blood protein levels are used to determine the level of free calcium unbound to protein. Increased blood uric acid levels may indicate gout. 

Nursing diagnosis Nursing Care Plans for Renal Calculi/Kidney stones
Common nursing diagnosis found in Nursing Care Plans for Renal Calculi/Kidney stones
Acute pain
Altered urinary elimination
Deficient knowledge (treatment plan)
Impaired urinary elimination
Ineffective tissue perfusion: Renal
Risk for imbalanced fluid volume
Risk for infection Risk for injury

Sample Nursing Care Plans for Renal Calculi/Kidney stones
Nursing diagnosis
Nursing outcome
Nursing Interventions
Evaluation
Acute pain related to inflammation, obstruction, and abrasion of urinary tract by migration of stones

·        Verbalizes reduced pain level

·        Administer prescribed  analgesic
·        Encourage patient to assume position that brings some relief.
·        Reassess pain frequently using pain scale.
·        Administer antiemetic  as indicated for nausea
·        Position the patient for comfort

Altered urinary elimination


Urinary Elimination:
Ability of the urinary system to filter wastes, conserve solutes, and
collect and discharge urine in a healthy pattern

Urinary Continence: Control of the elimination of urine
Self-Care: Toileting: Ability to toilet self
Assess degree of interference/disability
·       Determine client’s previous pattern of elimination and compare with current situation.
·                Frequency,
·                Urgency,
·                Burning,
·                Incontinence,
·                Nocturia/enuresis,
·                Size and force of urinary stream.
·       Provides information about degree of interference with elimination or may indicate bladder infection

·       Palpate bladder to assess retention. Fullness over bladder following voiding is indicative of inadequate emptying/retention and requires intervention.
·       Investigate pain which may be indicative of infection:
·                location,
·                duration,
·                 intensity;
·                Presence of bladder spasms, back or flank pain, etc.,.
·      Determine client’s usual daily fluid intake
Verbalize understanding of condition.
● Identify causative factors. (Refer to specific NDs for incontinence/retention as appropriate.)
● Achieve normal elimination pattern or participate in measures to correct/compensate for
defects.
● Demonstrate behaviors/techniques to prevent urinary infection.
● Manage care of urinary catheter, or stoma and appliance following urinary diversion.

Saturday, February 20, 2010

The diagnosis of delusional disorder can be made when a person exhibits non-bizarre delusions of at least 1 month duration that cannot be attributed to other psychiatric disorders. Non-bizarre delusions must be about phenomena that, although not real, are within the realm of being possible. In general, the patient’s delusions are well systematized and have been logically developed. The person’s behavioral and emotional responses to the delusions appear to be appropriate. Usually the person’s functioning and personality are well preserved and show minimal deterioration if at all. 
Characteristics of delusional disorder

  • Non-bizarre delusions of at least 1 month’s duration 
  • No positive or negative symptoms of schizophrenia present 
  • Tactile or olfactory hallucinations may be present and related to the delusional theme 
  • Functioning not markedly impaired and behavior not obviously bizarre or odd 
  • Only brief mood episodes, if any 
  • Not due to direct physiologic effects of a chemical or a general medical condition 


Etiology of delusional disorder 
Etiology of the delusional disorder is unknown. Risk factors associated with the disorder include advanced age, sensory impairment/isolation, family history, social isolation, personality features (e.g. unusual interpersonal sensitivity), and recent immigration. Some have reported higher association of delusional disorder with widowhood, celibacy, and history of substance abuse. Age of onset is later than schizophrenia and earlier in men compared to women. 

Subtypes of delusional disorder 

Persecutory Type 
Here the person affected believes that he or she is being followed, spied on, poisoned or drugged, harassed, or conspired against. The person affected may get preoccupied by small slights that can become incorporated into the delusional system. These individuals may resort to legal actions to remedy perceived injustice. Individuals suffering from these delusions often become resentful and angry with a potential to get violent against those believed to be against them. 

Jealous Type 
Individuals with this subtype have the delusional belief that their spouses/lovers are unfaithful. Jealousy is a powerful emotion and when it occurs in delusional disorder or as part of another condition, it can be potentially dangerous and has been associated with violence including suicidal and homicidal behavior. Delusions of infi delity have also been called conjugal paranoia . The term Othello syndrome has been used to describe morbid jealousy. 

Erotomanic Type 
Persons with delusional disorder of the erotomanic type have delusions of being loved by another. The patient believes that a perceived suitor, usually more socially prominent than herself, is in love with her. Erotomania shares many features with, is derived from, and is often referred to as de Clerambault’s syndrome. 

Somatic Type 
Delusional disorder with somatic delusions has been called monosymptomatic hypochondriacal psychosis . This disorder differs from other conditions with hypochondriacal symptoms in degree of reality impairment. Munro ( 1991 ) has described the largest series of cases and has used content of delusions to defi ne three main types: 
Delusions of Infestations (Including Parasitosis). 
Delusional parasitosis has been described in association with many physical illnesses such as vitamin B 12 defi ciency, pellagra, neurosyphilis, multiple sclerosis, thalamic dysfunction, hypophyseal tumors, diabetes mellitus, severe renal disease, hepatitis, hypothyroidism, mediastinal lymphoma, and leprosy. Use of cocaine and presence of dementia has also been reported. Psychogenic parasitosis was also known as Ekbom’s syndrome before being referred to as delusional parasitosis . 
Delusions of Dysmorphophobia 
This condition includes delusions such as of misshapenness, personal ugliness, or exaggerated size of body parts. 
Delusions of Foul Body Odors or Halitosis. 
This is also called olfactory reference syndrome. 

Grandiose Type 
This is also referred to as megalomania . In this subtype, the central theme of the delusion is the grandiosity of having made some important discovery or having great talent. Sometimes there may be a religious theme to the delusional thinking such that the person believes that he or she has a special message from god. 

Mixed Type 
This subtype is reserved for those with two or more delusional themes. However, it should be used only where it is difficult to clearly discern one theme of delusion. This subtype is used for cases in which the predominant delusion cannot be subtyped within the above mentioned categories. A possible example is certain delusions of misidentification, for example, Capgras’s syndrome , named after the French psychiatrist who described the ‘illusions of doubles.’ The delusion here is the belief that a familiar person has been replaced by an imposter. A variant of this is Fregoli’s syndrome where the delusion is that the persecutors or familiar persons can assume the guise of strangers and the very rare delusion that familiar persons could change themselves into other persons at will (intermetamorphosis). 

COMPLICATIONS of delusional disorder If left undiagnosed, untreated, or ineffectively treated, schizophrenia can lead to profound inability to function and contribute to the problem of homelessness in our society. Neglect of other medical conditions; therefore, complications due to untreated medical illness are common. Depression and suicide. Substance use, abuse, or dependency. 

Nursing Diagnosis Delusional Disorder 
Nursing Diagnosis for Delusional Disorder determine from what we found in Nursing Assessment Nursing Care Plans for Delusional Disorder. 

Nursing assessment nursing care Plans for Delusional Disorders Assess for positive symptoms of schizophrenia. These symptoms reflect aberrant mental activity and are usually present early in the first phase of the schizophrenic illness. 
Alterations in Thinking 

  • Delusion: false, fixed belief that is not amenable to change by reasoning. The most frequent elicited delusions include: Ideas of reference. Delusions of grandeur. Delusions of jealousy. Delusions of persecution. Somatic delusions. 
  • Loose associations: the thought process becomes illogical and confused. 
  • Neologisms: made-up words that have a special meaning to the delusional person. 
  • Concrete thinking: an overemphasis on small or specific details and an impaired ability to abstract. 
  • Echolalia: pathologic repeating of another’s words. 
  • Clang associations: the meaningless rhyming of a word in a forceful way. 
  • Word salad: a mixture of words that is meaningless to the listener. 


Alterations in Behavioral Responses 

  • Bizarre behavioral patterns Motor agitation and restlessness Automatic obedience or robotlike movement Autonomic obedience or robotlike movement Negativism Stereotyped behaviors Stupor Waxy flexibility (allowing another person to reposition extremities) 
  • Agitated or impulsive behavior 
  • Assess for negative symptoms of schizophrenia that reflect a deficiency of mental functioning Alogia (lack of speech) Anergia ( inability to react) Anhedonia ( inability to experience pleasure) Avolition (lack of motivation or initiation) Poor social functioning Poverty of speech Social withdrawal Thought blocking 
  • Assess for associated symptoms of schizophrenia Substance use, abuse, or dependence Depression Fantasy Violent or aggressive behavior Water intoxication Withdrawal 


Common nursing diagnosis found in Nursing Care Plans for Delusional Disorder 

  • Disturbed Thought Processes related to perceptual and cognitive distortions, as demonstrated by suspiciousness, defensive behavior, and disruptions in thought
  • Social Isolation related to an inability to trust 
  • Activity Intolerance related to adverse reactions to psychopharmacologic drugs 
  • Ineffective Coping related to misinterpretation of environment and impaired communication ability 
  • Risk for Self-directed or Other-directed Violence related to delusional thinking and hallucinatory experiences 


Nursing Care Plans for Delusional Disorder 
Nursing Care Plans For Delusional Disorder, delusional disorder diagnosis can be made when a person exhibits nonbizarre delusions of at least 1 month duration that cannot be attributed to other psychiatric disorders. Nonbizarre delusions must be about phenomena that, although not real, are within the realm of being possible. In general, the patient’s delusions are well systematized and have been logically developed. The person’s behavioral and emotional responses to the delusions appear to be appropriate. Usually the person’s functioning and personality are well preserved and show minimal deterioration if at all. 

Nursing Care Plans Delusional Disorder with nursing diagnosis; Disturbed Thought Processes, Social Isolation, Activity Intolerance, Ineffective Coping, Risk for Self-directed or Other-directed Violence.
NURSING DIAGNOSE
NURSING OUTCOME
INTERVENTION
EVALUATION
Disturbed Thought Processes related to perceptual and cognitive distortions, as demonstrated by suspiciousness, defensive behavior, and disruptions in thought

Patient showed the Differentiation Between Delusions and Reality 
  • Provide patient with honest and consistent feedback in a nonthreatening manner.
  • Avoid challenging the content of patient's behaviors.
  • Focus interactions on patient's behaviors.
  • Administer drugs as prescribed while monitoring and documenting patient's response to the drug regimen.
  • Use simple and clear language when speaking with patient.
  • Explain all procedures, tests, and activities to patient before starting them, and provide written or video material for learning purposes.

Exhibits improved reality orientation, concentration, and attention span as demonstrated through speech and behavior
Social Isolation related to an inability to trust

Patient showed the Promoting Socialization
  • Encourage patient to talk about feelings in the context of a trusting, supportive relationship.
  • Allow patient time to reveal delusions to you without engaging in a power struggle over the content or the reality of the delusions.
  • Use a supportive, empathic approach to focus on patient's feelings about troubling events or conflicts.
  • Provide opportunities for socialization and encourage participation in group activities.
  • Be aware of patient's personal space and use touch judiciously.
  • Help patient to identify behaviors that alienate significant others and family members.

Communicates with family and staff in a clear manner without evidence of loose, dissociated thinking

Activity Intolerance related to adverse reactions to psychopharmacologic drugs

Patient showed the Improving Activity Tolerance
  • Assess patient's response to prescribed antipsychotic drug.
  • Collaborate with patient and occupational and physical therapy specialists to assess patient's ability to perform ADLs.
  • Collaborate with patient to establish a daily, achievable routine within physical limitations.
  • Teach strategies to manage adverse effects of antipsychotic drug that affect patient's functional status, including:
    • Change positions slowly
    • Gradually increase physical activities
    • Limit overdoing it in hot, sunny weather
    • Use sun precautions
    • Use caution in activities if extrapyramidal symptoms develop.

Independently maintains personal hygiene without fatigue
Ineffective Coping related to misinterpretation of environment and impaired communication ability

Patient showed the Improving Coping with Thoughts and Feelings

  • Encourage patient to express feelings.
  • Focus on patient's feelings and behavior.
  • Provide honest perceptions of reality and feedback about symptoms and behaviors.
  • Encourage patient to explore adaptive behaviors that increase abilities and success in socializing and accomplishing ADLs.
  • Decrease environmental stimuli.

Attends group activities

Risk for Self-directed or Other-directed Violence related to delusional thinking and hallucinatory experiences

Safety appears
  • Monitor patient for behaviors that indicate increased anxiety and agitation.
  • Collaborate with patient to identify anxious behaviors as well as the causes.
  • Tell patient that you will help with maintaining behavioral control.
  • Establish consistent limits on patient's behaviors and clearly communicate these limits to patient, family members, and health care providers.
  • Secure all potential weapons and articles from patient's room and the unit environment that could be used to inflict an injury.
  • To prepare for possible continued escalation, form a psychiatric emergency assist team and designate a leader to facilitate an effective and safe aggression-management process.
  • Determine the need for external control, including seclusion or restraints. Communicate the decision to patient and put plan into action.
  • Frequently monitor patient within the guidelines of facility's policy on restrictive devices and assess the patient's level of agitation.
  • When patient's level of agitation begins to decrease and self-control is regained, establish a behavioral agreement that identifies specific behaviors that indicate self-control against a reescalation of agitation.

Remains free from harm or violent acts

Wednesday, January 20, 2010

Nursing care Plans for Cirrhosis, Cirrhosis is a chronic hepatic disease that is characterized by destruction of the functional liver cells, which leads to cellular death. In cirrhosis, the damaged liver cells regenerate as fibrosis areas instead of functional cells, causing alterations in liver structure, function, blood circulation, and lymph damage. The major cellular changes include irreversible chronic injury of the functional liver tissue and the formation of regenerative nodules. These changes result in liver cell necrosis, collapse of liver support networks, distortion of the vascular bed, and nodular regeneration of the remaining liver cells. This disease alters liver structure and normal vasculature, impairs blood and lymph flow, and ultimately causes hepatic insufficiency.

Pathophysiology of Cirrhosis

Nursing care Plans for Cirrhosis
Treatment of Cirrhosis The goal of Cirrhosis therapy is to remove or alleviate the underlying cause of cirrhosis, prevent further liver damage, and prevent or treat complications:
  • Vitamins and nutritional supplements promote healing of damaged hepatic cells and improve the patient's nutritional status. 
  • Sodium consumption is usually restricted, and liquid intake is limited to or reduce to help manage ascites and edema. 
  • Drug therapy requires special caution detoxify harmful substances efficiently. 
  • Antacids may be prescribed to reduce gastric distress and decrease the potential for GI bleeding. 
  • Potassium-sparing diuretics, such as furosemide, may be used to reduce ascites and edema. 
  • Alcohol is restricted /prohibited,. 
  • Sedatives should be avoided. Acetaminophen is especially hepatotoxic, particularly when combined with alcohol. 
  • In patients with ascites, paracentesis may be used as a palliative treatment to relieve abdominal pressure. 
  • Surgical intervention may be required to divert ascites 
  • To control bleeding from esophageal varices or other GI hemorrhage, nonsurgical measures are attempted first. These include gastric intubation and esophageal balloon tamponade. In gastric intubation, a tube is inserted and the stomach is lavaged until the contents are clear. If the bleeding is assessed as a gastric ulcer, antacids and histamine antagonists are administered. 
Patient teaching and home healthcare guide Cirrhosis patients
  • Emphasize to the patient with alcoholic liver cirrhosis that continued alcohol use exacerbates the Cirrhosis disease. 
  • Emphasize to the patient that alcoholic liver disease in its early stages is reversible when the patient abstains from alcohol. but on further stage can be irreversible
  • To minimize the risk of bleeding, warn the patient against taking non-steroidal anti-inflammatory drugs, straining to defecate, and blowing his nose or sneezing too vigorously. Suggest using an electric razor and a soft toothbrush. 
  • Advise the patient that rest and good nutrition conserve energy and decrease metabolic demands on the liver. 
  • Teach the patient to have frequent, small meals. Teach him to alternate periods of rest and activity to reduce oxygen demand and prevent fatigue. 
  • Tell the patient how he can conserve energy while performing activities of daily living. For example, suggest that he sit on a bench while bathing or dressing. 
  • Stress the need to avoid infections and abstain from alcohol. Refer the patient to Alcoholics Anonymous, if appropriate 
  • Encourage the patient to seek frequent medical follow-up. Visits from a community health nurse to monitor the patient’s progress and to help with any questions or problems at home. 
  • Refer the patient to an alcohol support group or liver transplant support group 
Nursing care Plans for Cirrhosis
Cirrhosis is a chronic hepatic disease that is characterized by destruction of the functional liver cells, which leads to cellular death. In cirrhosis, the damaged liver cells regenerate as fibrosis areas instead of functional cells, causing alterations in liver structure, function, blood circulation, and lymph damage. The major cellular changes include irreversible chronic injury of the functional liver tissue and the formation of regenerative nodules. These changes result in liver cell necrosis, collapse of liver support networks, distortion of the vascular bed, and nodular regeneration of the remaining liver cells. This disease alters liver structure and normal vasculature, impairs blood and lymph flow, and ultimately causes hepatic insufficiency.

Causes for Cirrhosis depending on the type for Cirrhosis
Hepatocellular disease, Postnecrotic cirrhosis called portal, nutritional, or alcoholic cirrhosis stems from various types of hepatitis e.g. A, B, C, or D viral hepatitis or toxic exposures. Damage of the Livver results from malnutrition and overuse of alcohol. Fibrous tissue forms in portal areas and around central veins. Autoimmune disease, such as sarcoidosis and chronic inflammatory bowel disease, may result in cirrhosis.
Cholestatic diseases, Cholestatic diseases include diseases of the biliary tree and sclerosing cholangitis.
Metabolic diseases, metabolic diseases include disorders such as Wilson's disease, alpha1- antitrypsin deficiency, and hemochromatosis.
Other types of cirrhosis, other types of cirrhosis include Budd-Chiari syndrome, cardiac cirrhosis, and cryptogenic cirrhosis. Cardiac cirrhosis is rare; the liver damage results from rightsided heart failure. Cryptogenic refers to cirrhosis of unknown cause

Complications for Cirrhosis
  • Portal hypertension, 
  • Bleeding esophageal varices 
  • Hepatic encephalopathy 
  • Hepatorenal syndrome. 
Diagnostic tests for Cirrhosis
  • Liver biopsy 
  • Abdominal X-rays 
  • Computed tomography and liver scans 
  • Esophagogastroduodenoscopy 
  • Blood and Urine and stool studies disclose increased urine levels of bilirubin and urobilinogen; fecal urobilinogen levels decrease
Common Nursing diagnoses found on Nursing care Plans for Cirrhosis
  • Activity intolerance 
  • Disturbed thought processes 
  • Excess fluid volume
  • Hopelessness 
  • Imbalanced nutrition: Less than body requirements
  • Risk for deficient fluid volume 
  • Risk for impaired skin integrity 
  • Risk for injury Cirrhosis: 
Nursing Outcomes, Nursing Interventions, and Patient Teaching
Cirrhosis is a chronic hepatic disease that is characterized by destruction of the functional liver cells, which leads to cellular death. In cirrhosis, the damaged liver cells regenerate as fibrosis areas instead of functional cells, causing alterations in liver structure, function, blood circulation, and lymph damage. The major cellular changes include irreversible chronic injury of the functional liver tissue and the formation of regenerative nodules. These changes result in liver cell necrosis, collapse of liver support networks, distortion of the vascular bed, and nodular regeneration of the remaining liver cells. This disease alters liver structure and normal vasculature, impairs blood and lymph flow, and ultimately causes hepatic insufficiency.

Nursing Key outcomes nursing care Plans for Cirrhosis The patient will:

  • Perform ADL activities of daily living without excessive fatigue or exhaustion.
  • Remain oriented to his environment.
  • Show no signs of circulatory overload.
  • Participate in decisions about care.
  • Maintain adequate caloric intake.
  • Patient's fluid volume will remain within normal parameters.
  • Patient's skin integrity will remain intact.
  • Avoid or minimize complications. 


Nursing interventions nursing care Plans for Cirrhosis

  • Monitor vital signs, intake and output, and electrolyte levels to determine fluid volume status.
  • Assess fluid retention
  • Weigh the patient daily and document his weight. 
  • Administer diuretics, potassium, and protein or vitamin supplements as ordered.
  • Restrict sodium and fluid intake as ordered.
  • Assist and provide oral hygiene before and after meals. 
  • Determine food preferences and provide them within the patient's prescribed diet limitations. 
  • Provide frequent, small meals. 
  • Observe and document the degree of sclera and skin jaundice.  
  • Give the patient frequent skin care. 
  • Observe for bleeding gums, ecchymosed, epitasis, and petechiae. 
  • Inspect stools for amount, color, and consistency. 
  • Increase the patient's exercise tolerance by decreasing fluid volumes and providing rest periods before exercise. 
  • Use appropriate safety measures to protect the patient from injury.
  • Watch for signs of anxiety, epigastric fullness, restlessness, and weakness.
  • Observe closely for signs of behavioral or personality changes.
  • Observe Report increasing stupor, lethargy, hallucinations, or neuromuscular dysfunction. Arouse the patient periodically to determine level of consciousness. Watch for asterixis, a sign of developing encephalopathy. 
  • Allow the patient to express his feelings about having cirrhosis. 
  • Provide psychological support and encouragement, when appropriate. 


Patient teaching nursing care Plans for Cirrhosis

  • Warn the patient against taking nonsteroidal anti-inflammatory drugs, straining to defecate, and blowing his nose or sneezing too vigorously. To minimize the risk of bleeding, 
  • Suggest using a soft toothbrush and a electric razor 
  • Advise the patient that rest and good nutrition conserve energy and decrease metabolic demands on the liver. 
  • Suggest the patient to eat frequent, small meals. Teach him to alternate periods of rest and activity to reduce oxygen demand and prevent fatigue.
  • Tell the patient how he can conserve energy while performing activities of daily living. For example, suggest that he sit on a bench while bathing or dressing. 
  • Stress the need to avoid infections and abstain from alcohol. Refer the patient to alcohol abuse treatment Anonymous, if appropriate 
  • Alcohol abuse treatment. Emphasize to the patient with alcoholic liver cirrhosis that continued alcohol use exacerbates the disease. Stress that alcoholic liver disease in its early stages is reversible when the patient abstains from alcohol. Encourage family involvement in. Assist the patient in obtaining counseling or support for her or his alcoholism. 
  • Encourage the patient to seek frequent medical follow-up 
  • Refer the patient to an alcohol support group or liver transplant support group.

Wednesday, January 13, 2010

Traumatic Amputation
Nursing Care Plans for Traumatic Amputation. Traumatic amputation the accidental loss of a body part usually involves a finger, toe, arm, or leg. In complete amputation, the member is totally severed; in partial amputation, some soft-tissue connection remains. The prognosis for traumatic amputation has improved because of early, improved emergency and critical care management, new surgical techniques, early rehabilitation, prosthesis fitting, and new prosthesis designs. Amputations can be surgical (therapeutic) or traumatic (emergencies resulting from injury).
Causes for Traumatic Amputation
A traumatic amputation may result from a cutting, tearing, or crushing insult involving the use of factory, farm, or power tools, or from a motor vehicle accident.

Complications for Traumatic Amputation
Hypovolemic shock and sepsis are possible complications in traumatic amputation. If reimplantation is attempted, residual paralysis may occur.

Levels of Amputation
Below the knee
Syme procedure
Transmetatarsal/toe Amputation
Hip disarticulation/extensive hemipelvectomy
Upper extremity Nursing assessment

Nursing Care Plans for Traumatic Amputation
Patient history reveals the type of accident that caused the amputation. Inspection: partially or completely severed body lost, hemorrhage and soft tissue damage, type of wound well-defined edges and damage is local/ crush amputation, damage involves the tissue and arterial. Psychosocial: patient with a traumatic amputation may be in the denial phase of grief
Traumatic Amputation
Treatment Blood loss and hypovolemic shock is the greatest immediate threat in traumatic amputation. Control bleeding, Fluid replacement with sterile normal saline or lactated ringer’s solution, colloids, and Blood replacement as needed. Reimplantation Early prosthesis fitting and rehabilitation.

Nursing diagnosis Nursing Care Plans for Amputation
Common Nursing diagnosis found in Nursing Care Plans for Traumatic Amputation:
Acute pain
Deficient fluid volume
Disturbed body image
Dressing or grooming self-care deficit
Fear
Hopelessness
Impaired physical mobility
Impaired skin integrity
Ineffective coping
Ineffective role performance
Ineffective tissue perfusion: Peripheral
Risk for disuse syndrome
Risk for infection
Risk for post trauma syndrome

Nursing key outcomes, Interventions and patient teaching Nursing Care Plans for Traumatic Amputation

Monday, January 11, 2010

Nursing Care Plans For Appendicitis, Appendicitis is an acute inflammation of the vermiform appendix, a narrow, blind tube that extends from the inferior part of the cecum just below the ileocecal valve. Although the appendix has no known function, it does regularly fill and empty itself of food. Appendicitis occurs when the appendix becomes inflamed from ulceration of the mucosa or obstruction of the lumen. If untreated, this disease is fatal.

Causes For Appendicitis 
Obstruction of the vermiform appendix. Since the appendix is a small, finger-like Appendage of the cecum, it is prone to obstruction as it regularly fills and empties with intestinal contents. obstruction caused by a fecal mass, stricture, barium ingestion, or viral infection. This obstruction sets off an inflammatory process that can lead to infection, thrombosis, necrosis, and perforation.

Complications For Appendicitis 
Common complication of appendicitis: Appendix ruptures or Perforates. Peritonitis. Other complications include: Appendiceal abscess Pyelophlebitis.

Diagnostik tes 
Complete blood count Abdominal ultrasound Abdominal computed tomography (CT) scan

Nursing Assessment Nursing Care Plans For Appendicitis 
Because other disorders can mimic appendicitis in sign and symptoms, diagnosis must rule out illnesses with similar symptoms: bladder infection, gastroenteritis, ileitis, colitis, acute salpingitis, tubo-ovarian abscess, diverticulitis, gastritis, ovarian cyst, pancreatitis, renal colic, and uterine disease
Patients history of midabdominal pain as the disease process progresses, patients usually complain of a constant epigastric or periumbilical pain that eventually localizes in the right lower quadrant of the abdomen. The patient may also report anorexia, nausea, one or two episodes of vomiting, and a low-grade fever. Later signs and symptoms include malaise, constipation and, rarely, diarrhea. Inspection typically shows a patient who walks bent over to reduce right lower quadrant pain. When sleeping or lying in a supine position, he may keep his right knee bent up to decrease pain. Auscultation usually reveals normal bowel sounds. Palpation and percussion disclose no localized abdominal findings except diffuse tenderness in the midepigastric area and around the umbilicus. Tenderness in the right lowers abdominal. There may be pain in the right lower quadrant resulting from palpating the lower left quadrant (Rovsing’s sign).

Appendicitis Treatment 
Appendectomy If peritonitis develops, treatment involves GI intubation, parenteral replacement of fluids and electrolytes, and administration of antibiotics.

Nursing diagnosis Nursing Care Plans For Appendicitis 
Common nursing diagnosis found in Nursing Care Plans For Appendicitis

  • Acute pain 
  • Imbalanced nutrition: Less than body requirements 
  • Impaired skin integrity 
  • Ineffective tissue perfusion: GI 
  • Risk for deficient fluid volume 
  • Risk for infection 
  • Risk for injury 


Nursing Key outcomes, Interventions and patients teaching Nursing Care Plans for Appendicitis

Saturday, January 9, 2010

Respiratory System
Respiratory System
Nursing Care Plans for Pneumonia. Pneumonia, acute infection of the lung parenchyma, interstitial lung tissue in which fluid and blood cells escape into the alveoli. that often impairs gas exchange. Pneumonia classified in several ways. 
Based on microbiological etiology origin: Viral Bacterial Fungal Protozoa Mycobacterium Mycoplasmal Rickettsial 
Based in location, pneumonia can be classified: Bronchopneumonia, Bronchopneumonia involves distal airways and alveoli Lobular pneumonia or lobar pneumonia. In this pneumonia involves part of a lobe; and lobar pneumonia, an entire lobe 

The infection is also classified as one of three types: 

  • Primary pneumonia, Primary pneumonia results directly from inhalation or aspiration of a pathogen, such as bacteria or a virus; it includes pneumococcal and viral pneumonia. 
  • Secondary pneumonia, Secondary pneumonia may follow initial lung damage from a noxious chemical or other insult (superinfection) or may result from hematogenous spread of bacteria from a distant area. 
  • Aspiration pneumonia, Aspiration pneumonia results from inhalation of foreign matter, such as stomach contents vomitus or food particles, into the bronchi. It’s more likely to occur in elderly or debilitated patients, those receiving nasogastric tube feedings, higher prevalence those with an impaired gag reflex, poor oral hygiene, or a decreased level of consciousness 

Causes for pneumonia 

  • In bacterial pneumonia, the most common cause of bacterial pneumonia in adults is a bacteria called Streptococcus pneumoniae or Pneumococcus. Usually occurs when the lungs’ defense mechanisms are impaired by such factors as suppressed cough reflex, decreased cilia action, decreased activity of phagocytic cells, and the accumulation of secretions. Pneumococcal pneumonia occurs only in the lobar form.which can occur in any part of the lungs, an infection initially triggers alveolar inflammation and edema. As the alveolocapillary membrane breaks down, alveoli fill with blood and exudate, resulting in atelectasis. In severe bacterial infections, the lungs assume a heavy, liverlike appearance, as in acute respiratory distress syndrome (ARDS). 
  • Viral pneumonia occurs when a virus attacks bronchiolar epithelial cells and causes interstitial inflammation and desquamation, which eventually spread to the alveoli 
  • In aspiration pneumonia, aspiration of gastric juices or hydrocarbons triggers similar inflammatory changes and inactivates surfactant over a large area. Decreased surfactant leads to alveolar collapse. Acidic gastric juices may directly damage the airways and alveoli. Particles with the aspirated gastric juices may obstruct the airways and reduce airflow. 

Predisposing factors increase the risk of pneumonia. 
For bacterial and viral pneumonia, these include chronic illness and debilitation, Cancer (particularly lung cancer) Abdominal and thoracic surgery Atelectasis Common colds or other viral respiratory infections Chronic respiratory disease (chronic obstructive pulmonary disease, asthma, bronchiectasis, cystic fibrosis), influenza, Smoking, Malnutrition, Alcoholism, Sickle cell disease, Tracheotomy, exposure to noxious gases Immunosuppressive therapy. 

Complications for Pneumonia 
Without proper treatment, pneumonia can lead to such life-threatening complications as Septic shock, Hypoxemia, and Respiratory failure. Empyema or lung abscess. Bacteremia Endocarditi Pericarditis Meningitis 

Diagnostic tests 
Chest X-rays. Sputum specimen for Gram stain and culture and sensitivity. White blood cell count Blood cultures. Arterial blood gas (ABG). Bronchoscopy or transtracheal aspiration. Pleural fluid culture. Pulse oximetry. 

Nursing Assessment Nursing Care Plans for Pneumonia 
Focused Nursing assessment in pneumonia care plans Vital sign: blood pressure, body temperature, the pulse or rate of heartbeats, the respiration or rate of breathing Crackles, wheezing, or rhonchi over the affected lung area Dullness when you percuss Presence of cyanosis, and presence of dyspnea or tachypnea
Patient’s history The patient may have a history of a recent upper respiratory infection, influenza, or a viral syndrome. Elicit a history of a chronic pulmonary disease, such as asthma, bronchitis, or tuberculosis; prolonged immobility; sickle cell anemia; neurological disorders that cause paralysis of the diaphragm; surgery of the thorax or abdomen; smoking; alcoholism; IV drug therapy or abuse; and malnutrition. Establish any history of exposure to noxious gases, aspiration, or immunosuppressive therapy Bacterial pneumonia, the patient may report pleuritic chest pain, a cough, excessive sputum production, and chills. On Nursing assessment, you may note that the patient has a fever. In inspection, you may found that the patient is shaking and coughs up sputum. In advanced cases of all types of pneumonia, you hear dullness when you percuss. Auscultation may disclose crackles, wheezing, or rhonchi over the affected lung area as well as decreased breath sounds and decreased vocal fremitus. 

Nursing diagnosis Nursing Care Plans for Pneumonia 
Common Nursing Diagnosis found in Nursing Care Plans for Pneumonia 

  • Ineffective airway clearance 
  • Acute pain 
  • Anxiety 
  • Hyperthermia 
  • Imbalanced nutrition: Less than body requirements 
  • Impaired gas exchange 
  • Ineffective coping 
  • Risk for deficient fluid volume 
  • Risk for infection 


Nursing Key outcomes, interventions and patient teaching Nursing Care Plans for Pneumonia